
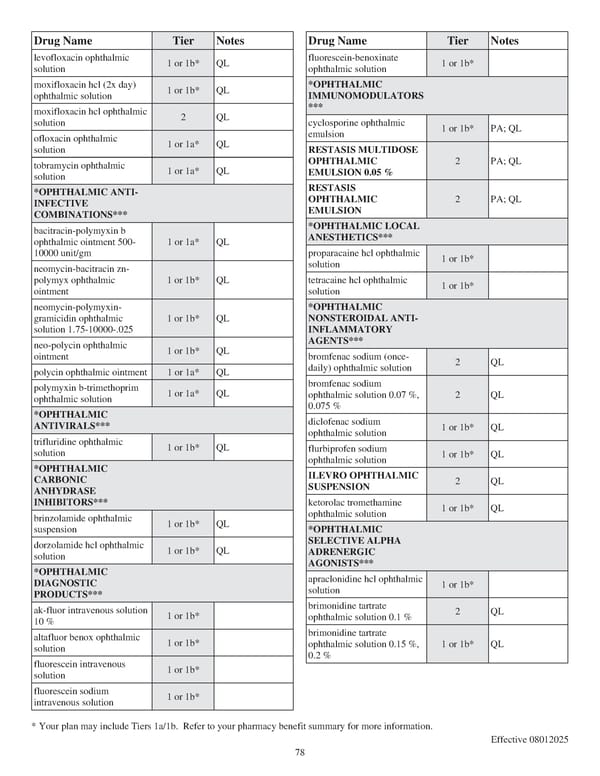
Drug Name Tier Notes levofloxacin ophthalmic solution 1 or 1b* QL moxifloxacin hcl (2x day) ophthalmic solution 1 or 1b* QL moxifloxacin hcl ophthalmic solution 2 QL ofloxacin ophthalmic solution 1 or 1a* QL tobramycin ophthalmic solution 1 or 1a* QL *OPHTHALMIC ANTI- INFECTIVE COMBINATIONS*** bacitracin-polymyxin b ophthalmic ointment 500- 10000 unit/gm 1 or 1a* QL neomycin-bacitracin zn- polymyx ophthalmic ointment 1 or 1b* QL neomycin-polymyxin- gramicidin ophthalmic solution 1.75-10000-.025 1 or 1b* QL neo-polycin ophthalmic ointment 1 or 1b* QL polycin ophthalmic ointment 1 or 1a* QL polymyxin b-trimethoprim ophthalmic solution 1 or 1a* QL *OPHTHALMIC ANTIVIRALS*** trifluridine ophthalmic solution 1 or 1b* QL *OPHTHALMIC CARBONIC ANHYDRASE INHIBITORS*** brinzolamide ophthalmic suspension 1 or 1b* QL dorzolamide hcl ophthalmic solution 1 or 1b* QL *OPHTHALMIC DIAGNOSTIC PRODUCTS*** ak-fluor intravenous solution 10 % 1 or 1b* altafluor benox ophthalmic solution 1 or 1b* fluorescein intravenous solution 1 or 1b* fluorescein sodium intravenous solution 1 or 1b* Drug Name Tier Notes fluorescein-benoxinate ophthalmic solution 1 or 1b* *OPHTHALMIC IMMUNOMODULATORS *** cyclosporine ophthalmic emulsion 1 or 1b* PA; QL RESTASIS MULTIDOSE OPHTHALMIC EMULSION 0.05 % 2 PA; QL RESTASIS OPHTHALMIC EMULSION 2 PA; QL *OPHTHALMIC LOCAL ANESTHETICS*** proparacaine hcl ophthalmic solution 1 or 1b* tetracaine hcl ophthalmic solution 1 or 1b* *OPHTHALMIC NONSTEROIDAL ANTI- INFLAMMATORY AGENTS*** bromfenac sodium (once- daily) ophthalmic solution 2 QL bromfenac sodium ophthalmic solution 0.07 %, 0.075 % 2 QL diclofenac sodium ophthalmic solution 1 or 1b* QL flurbiprofen sodium ophthalmic solution 1 or 1b* QL ILEVRO OPHTHALMIC SUSPENSION 2 QL ketorolac tromethamine ophthalmic solution 1 or 1b* QL *OPHTHALMIC SELECTIVE ALPHA ADRENERGIC AGONISTS*** apraclonidine hcl ophthalmic solution 1 or 1b* brimonidine tartrate ophthalmic solution 0.1 % 2 QL brimonidine tartrate ophthalmic solution 0.15 %, 0.2 % 1 or 1b* QL * Your plan may include Tiers 1a/1b. Refer to your pharmacy benefit summary for more information. Effective 08012025 78
 Anthem PPO & HDHP Essential Drug List Page 77 Page 79