
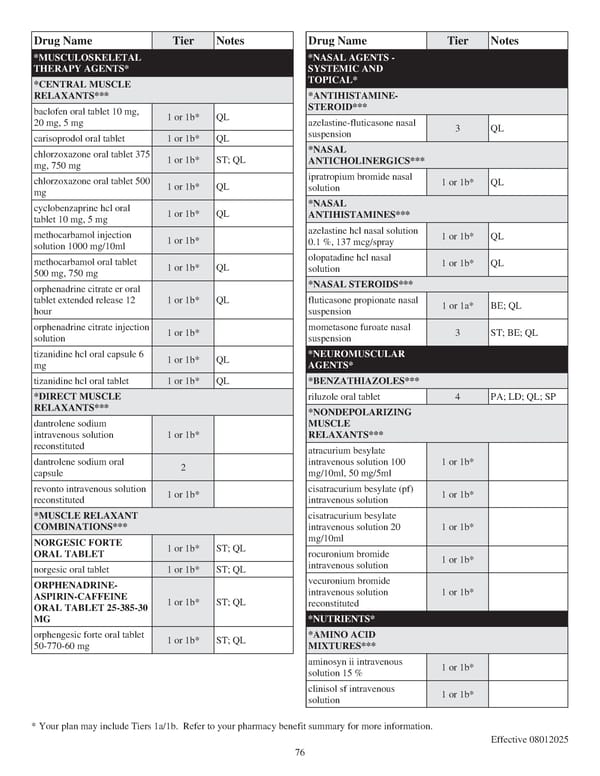
Drug Name Tier Notes *MUSCULOSKELETAL THERAPY AGENTS* *CENTRAL MUSCLE RELAXANTS*** baclofen oral tablet 10 mg, 20 mg, 5 mg 1 or 1b* QL carisoprodol oral tablet 1 or 1b* QL chlorzoxazone oral tablet 375 mg, 750 mg 1 or 1b* ST; QL chlorzoxazone oral tablet 500 mg 1 or 1b* QL cyclobenzaprine hcl oral tablet 10 mg, 5 mg 1 or 1b* QL methocarbamol injection solution 1000 mg/10ml 1 or 1b* methocarbamol oral tablet 500 mg, 750 mg 1 or 1b* QL orphenadrine citrate er oral tablet extended release 12 hour 1 or 1b* QL orphenadrine citrate injection solution 1 or 1b* tizanidine hcl oral capsule 6 mg 1 or 1b* QL tizanidine hcl oral tablet 1 or 1b* QL *DIRECT MUSCLE RELAXANTS*** dantrolene sodium intravenous solution reconstituted 1 or 1b* dantrolene sodium oral capsule 2 revonto intravenous solution reconstituted 1 or 1b* *MUSCLE RELAXANT COMBINATIONS*** NORGESIC FORTE ORAL TABLET 1 or 1b* ST; QL norgesic oral tablet 1 or 1b* ST; QL ORPHENADRINE- ASPIRIN-CAFFEINE ORAL TABLET 25-385-30 MG 1 or 1b* ST; QL orphengesic forte oral tablet 50-770-60 mg 1 or 1b* ST; QL Drug Name Tier Notes *NASAL AGENTS - SYSTEMIC AND TOPICAL* *ANTIHISTAMINE- STEROID*** azelastine-fluticasone nasal suspension 3 QL *NASAL ANTICHOLINERGICS*** ipratropium bromide nasal solution 1 or 1b* QL *NASAL ANTIHISTAMINES*** azelastine hcl nasal solution 0.1 %, 137 mcg/spray 1 or 1b* QL olopatadine hcl nasal solution 1 or 1b* QL *NASAL STEROIDS*** fluticasone propionate nasal suspension 1 or 1a* BE; QL mometasone furoate nasal suspension 3 ST; BE; QL *NEUROMUSCULAR AGENTS* *BENZATHIAZOLES*** riluzole oral tablet 4 PA; LD; QL; SP *NONDEPOLARIZING MUSCLE RELAXANTS*** atracurium besylate intravenous solution 100 mg/10ml, 50 mg/5ml 1 or 1b* cisatracurium besylate (pf) intravenous solution 1 or 1b* cisatracurium besylate intravenous solution 20 mg/10ml 1 or 1b* rocuronium bromide intravenous solution 1 or 1b* vecuronium bromide intravenous solution reconstituted 1 or 1b* *NUTRIENTS* *AMINO ACID MIXTURES*** aminosyn ii intravenous solution 15 % 1 or 1b* clinisol sf intravenous solution 1 or 1b* * Your plan may include Tiers 1a/1b. Refer to your pharmacy benefit summary for more information. Effective 08012025 76
 Anthem PPO & HDHP Essential Drug List Page 75 Page 77