
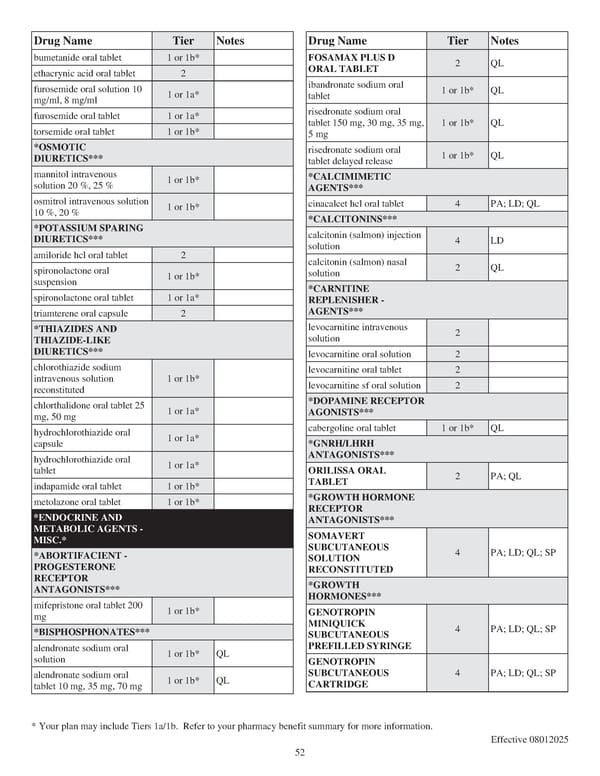
Drug Name Tier Notes bumetanide oral tablet 1 or 1b* ethacrynic acid oral tablet 2 furosemide oral solution 10 mg/ml, 8 mg/ml 1 or 1a* furosemide oral tablet 1 or 1a* torsemide oral tablet 1 or 1b* *OSMOTIC DIURETICS*** mannitol intravenous solution 20 %, 25 % 1 or 1b* osmitrol intravenous solution 10 %, 20 % 1 or 1b* *POTASSIUM SPARING DIURETICS*** amiloride hcl oral tablet 2 spironolactone oral suspension 1 or 1b* spironolactone oral tablet 1 or 1a* triamterene oral capsule 2 *THIAZIDES AND THIAZIDE-LIKE DIURETICS*** chlorothiazide sodium intravenous solution reconstituted 1 or 1b* chlorthalidone oral tablet 25 mg, 50 mg 1 or 1a* hydrochlorothiazide oral capsule 1 or 1a* hydrochlorothiazide oral tablet 1 or 1a* indapamide oral tablet 1 or 1b* metolazone oral tablet 1 or 1b* *ENDOCRINE AND METABOLIC AGENTS - MISC.* *ABORTIFACIENT - PROGESTERONE RECEPTOR ANTAGONISTS*** mifepristone oral tablet 200 mg 1 or 1b* *BISPHOSPHONATES*** alendronate sodium oral solution 1 or 1b* QL alendronate sodium oral tablet 10 mg, 35 mg, 70 mg 1 or 1b* QL Drug Name Tier Notes FOSAMAX PLUS D ORAL TABLET 2 QL ibandronate sodium oral tablet 1 or 1b* QL risedronate sodium oral tablet 150 mg, 30 mg, 35 mg, 5 mg 1 or 1b* QL risedronate sodium oral tablet delayed release 1 or 1b* QL *CALCIMIMETIC AGENTS*** cinacalcet hcl oral tablet 4 PA; LD; QL *CALCITONINS*** calcitonin (salmon) injection solution 4 LD calcitonin (salmon) nasal solution 2 QL *CARNITINE REPLENISHER - AGENTS*** levocarnitine intravenous solution 2 levocarnitine oral solution 2 levocarnitine oral tablet 2 levocarnitine sf oral solution 2 *DOPAMINE RECEPTOR AGONISTS*** cabergoline oral tablet 1 or 1b* QL *GNRH/LHRH ANTAGONISTS*** ORILISSA ORAL TABLET 2 PA; QL *GROWTH HORMONE RECEPTOR ANTAGONISTS*** SOMAVERT SUBCUTANEOUS SOLUTION RECONSTITUTED 4 PA; LD; QL; SP *GROWTH HORMONES*** GENOTROPIN MINIQUICK SUBCUTANEOUS PREFILLED SYRINGE 4 PA; LD; QL; SP GENOTROPIN SUBCUTANEOUS CARTRIDGE 4 PA; LD; QL; SP * Your plan may include Tiers 1a/1b. Refer to your pharmacy benefit summary for more information. Effective 08012025 52
 Anthem PPO & HDHP Essential Drug List Page 51 Page 53