
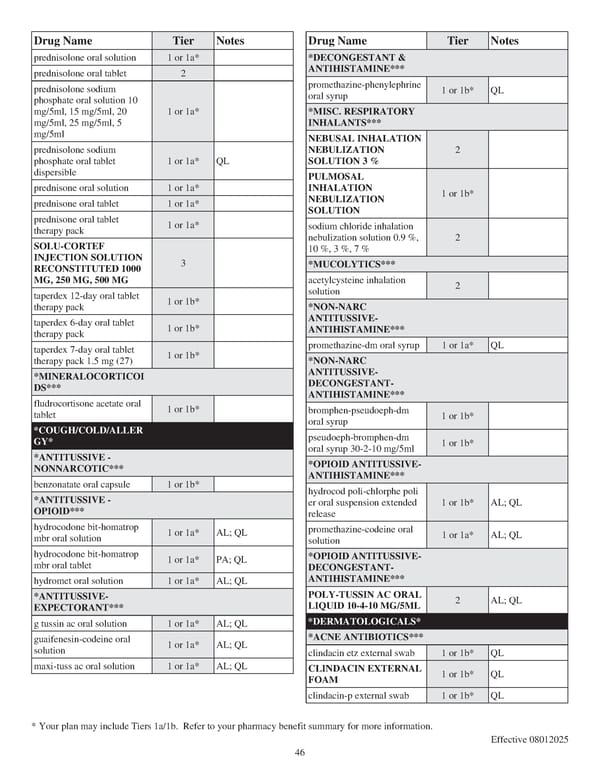
Drug Name Tier Notes prednisolone oral solution 1 or 1a* prednisolone oral tablet 2 prednisolone sodium phosphate oral solution 10 mg/5ml, 15 mg/5ml, 20 mg/5ml, 25 mg/5ml, 5 mg/5ml 1 or 1a* prednisolone sodium phosphate oral tablet dispersible 1 or 1a* QL prednisone oral solution 1 or 1a* prednisone oral tablet 1 or 1a* prednisone oral tablet therapy pack 1 or 1a* SOLU-CORTEF INJECTION SOLUTION RECONSTITUTED 1000 MG, 250 MG, 500 MG 3 taperdex 12-day oral tablet therapy pack 1 or 1b* taperdex 6-day oral tablet therapy pack 1 or 1b* taperdex 7-day oral tablet therapy pack 1.5 mg (27) 1 or 1b* *MINERALOCORTICOI DS*** fludrocortisone acetate oral tablet 1 or 1b* *COUGH/COLD/ALLER GY* *ANTITUSSIVE - NONNARCOTIC*** benzonatate oral capsule 1 or 1b* *ANTITUSSIVE - OPIOID*** hydrocodone bit-homatrop mbr oral solution 1 or 1a* AL; QL hydrocodone bit-homatrop mbr oral tablet 1 or 1a* PA; QL hydromet oral solution 1 or 1a* AL; QL *ANTITUSSIVE- EXPECTORANT*** g tussin ac oral solution 1 or 1a* AL; QL guaifenesin-codeine oral solution 1 or 1a* AL; QL maxi-tuss ac oral solution 1 or 1a* AL; QL Drug Name Tier Notes *DECONGESTANT & ANTIHISTAMINE*** promethazine-phenylephrine oral syrup 1 or 1b* QL *MISC. RESPIRATORY INHALANTS*** NEBUSAL INHALATION NEBULIZATION SOLUTION 3 % 2 PULMOSAL INHALATION NEBULIZATION SOLUTION 1 or 1b* sodium chloride inhalation nebulization solution 0.9 %, 10 %, 3 %, 7 % 2 *MUCOLYTICS*** acetylcysteine inhalation solution 2 *NON-NARC ANTITUSSIVE- ANTIHISTAMINE*** promethazine-dm oral syrup 1 or 1a* QL *NON-NARC ANTITUSSIVE- DECONGESTANT- ANTIHISTAMINE*** bromphen-pseudoeph-dm oral syrup 1 or 1b* pseudoeph-bromphen-dm oral syrup 30-2-10 mg/5ml 1 or 1b* *OPIOID ANTITUSSIVE- ANTIHISTAMINE*** hydrocod poli-chlorphe poli er oral suspension extended release 1 or 1b* AL; QL promethazine-codeine oral solution 1 or 1a* AL; QL *OPIOID ANTITUSSIVE- DECONGESTANT- ANTIHISTAMINE*** POLY-TUSSIN AC ORAL LIQUID 10-4-10 MG/5ML 2 AL; QL *DERMATOLOGICALS* *ACNE ANTIBIOTICS*** clindacin etz external swab 1 or 1b* QL CLINDACIN EXTERNAL FOAM 1 or 1b* QL clindacin-p external swab 1 or 1b* QL * Your plan may include Tiers 1a/1b. Refer to your pharmacy benefit summary for more information. Effective 08012025 46
 Anthem PPO & HDHP Essential Drug List Page 45 Page 47