
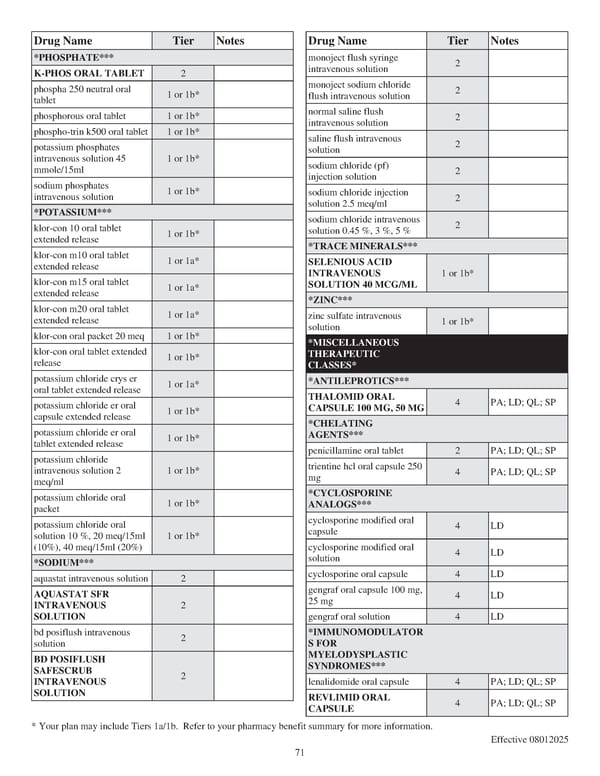
Drug Name Tier Notes *PHOSPHATE*** K-PHOS ORAL TABLET 2 phospha 250 neutral oral tablet 1 or 1b* phosphorous oral tablet 1 or 1b* phospho-trin k500 oral tablet 1 or 1b* potassium phosphates intravenous solution 45 mmole/15ml 1 or 1b* sodium phosphates intravenous solution 1 or 1b* *POTASSIUM*** klor-con 10 oral tablet extended release 1 or 1b* klor-con m10 oral tablet extended release 1 or 1a* klor-con m15 oral tablet extended release 1 or 1a* klor-con m20 oral tablet extended release 1 or 1a* klor-con oral packet 20 meq 1 or 1b* klor-con oral tablet extended release 1 or 1b* potassium chloride crys er oral tablet extended release 1 or 1a* potassium chloride er oral capsule extended release 1 or 1b* potassium chloride er oral tablet extended release 1 or 1b* potassium chloride intravenous solution 2 meq/ml 1 or 1b* potassium chloride oral packet 1 or 1b* potassium chloride oral solution 10 %, 20 meq/15ml (10%), 40 meq/15ml (20%) 1 or 1b* *SODIUM*** aquastat intravenous solution 2 AQUASTAT SFR INTRAVENOUS SOLUTION 2 bd posiflush intravenous solution 2 BD POSIFLUSH SAFESCRUB INTRAVENOUS SOLUTION 2 Drug Name Tier Notes monoject flush syringe intravenous solution 2 monoject sodium chloride flush intravenous solution 2 normal saline flush intravenous solution 2 saline flush intravenous solution 2 sodium chloride (pf) injection solution 2 sodium chloride injection solution 2.5 meq/ml 2 sodium chloride intravenous solution 0.45 %, 3 %, 5 % 2 *TRACE MINERALS*** SELENIOUS ACID INTRAVENOUS SOLUTION 40 MCG/ML 1 or 1b* *ZINC*** zinc sulfate intravenous solution 1 or 1b* *MISCELLANEOUS THERAPEUTIC CLASSES* *ANTILEPROTICS*** THALOMID ORAL CAPSULE 100 MG, 50 MG 4 PA; LD; QL; SP *CHELATING AGENTS*** penicillamine oral tablet 2 PA; LD; QL; SP trientine hcl oral capsule 250 mg 4 PA; LD; QL; SP *CYCLOSPORINE ANALOGS*** cyclosporine modified oral capsule 4 LD cyclosporine modified oral solution 4 LD cyclosporine oral capsule 4 LD gengraf oral capsule 100 mg, 25 mg 4 LD gengraf oral solution 4 LD *IMMUNOMODULATOR S FOR MYELODYSPLASTIC SYNDROMES*** lenalidomide oral capsule 4 PA; LD; QL; SP REVLIMID ORAL CAPSULE 4 PA; LD; QL; SP * Your plan may include Tiers 1a/1b. Refer to your pharmacy benefit summary for more information. Effective 08012025 71
 Anthem PPO & HDHP Essential Drug List Page 70 Page 72