
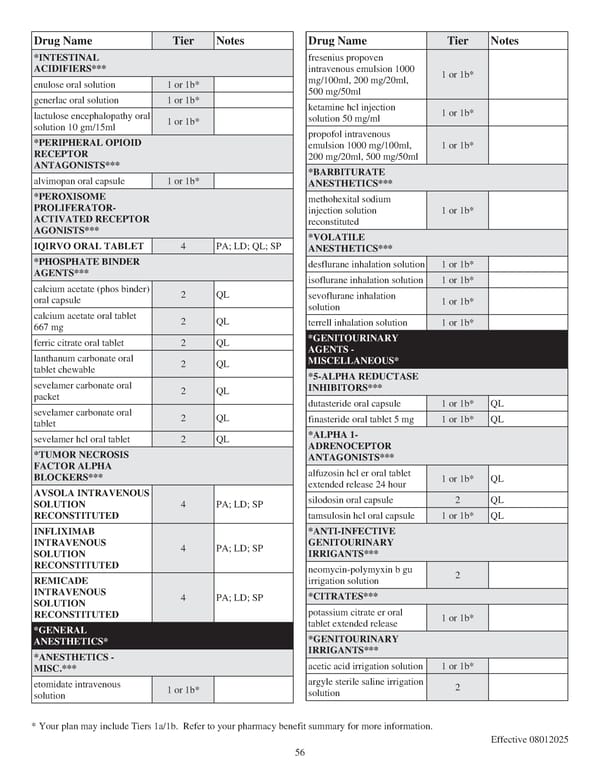
Drug Name Tier Notes *INTESTINAL ACIDIFIERS*** enulose oral solution 1 or 1b* generlac oral solution 1 or 1b* lactulose encephalopathy oral solution 10 gm/15ml 1 or 1b* *PERIPHERAL OPIOID RECEPTOR ANTAGONISTS*** alvimopan oral capsule 1 or 1b* *PEROXISOME PROLIFERATOR- ACTIVATED RECEPTOR AGONISTS*** IQIRVO ORAL TABLET 4 PA; LD; QL; SP *PHOSPHATE BINDER AGENTS*** calcium acetate (phos binder) oral capsule 2 QL calcium acetate oral tablet 667 mg 2 QL ferric citrate oral tablet 2 QL lanthanum carbonate oral tablet chewable 2 QL sevelamer carbonate oral packet 2 QL sevelamer carbonate oral tablet 2 QL sevelamer hcl oral tablet 2 QL *TUMOR NECROSIS FACTOR ALPHA BLOCKERS*** AVSOLA INTRAVENOUS SOLUTION RECONSTITUTED 4 PA; LD; SP INFLIXIMAB INTRAVENOUS SOLUTION RECONSTITUTED 4 PA; LD; SP REMICADE INTRAVENOUS SOLUTION RECONSTITUTED 4 PA; LD; SP *GENERAL ANESTHETICS* *ANESTHETICS - MISC.*** etomidate intravenous solution 1 or 1b* Drug Name Tier Notes fresenius propoven intravenous emulsion 1000 mg/100ml, 200 mg/20ml, 500 mg/50ml 1 or 1b* ketamine hcl injection solution 50 mg/ml 1 or 1b* propofol intravenous emulsion 1000 mg/100ml, 200 mg/20ml, 500 mg/50ml 1 or 1b* *BARBITURATE ANESTHETICS*** methohexital sodium injection solution reconstituted 1 or 1b* *VOLATILE ANESTHETICS*** desflurane inhalation solution 1 or 1b* isoflurane inhalation solution 1 or 1b* sevoflurane inhalation solution 1 or 1b* terrell inhalation solution 1 or 1b* *GENITOURINARY AGENTS - MISCELLANEOUS* *5-ALPHA REDUCTASE INHIBITORS*** dutasteride oral capsule 1 or 1b* QL finasteride oral tablet 5 mg 1 or 1b* QL *ALPHA 1- ADRENOCEPTOR ANTAGONISTS*** alfuzosin hcl er oral tablet extended release 24 hour 1 or 1b* QL silodosin oral capsule 2 QL tamsulosin hcl oral capsule 1 or 1b* QL *ANTI-INFECTIVE GENITOURINARY IRRIGANTS*** neomycin-polymyxin b gu irrigation solution 2 *CITRATES*** potassium citrate er oral tablet extended release 1 or 1b* *GENITOURINARY IRRIGANTS*** acetic acid irrigation solution 1 or 1b* argyle sterile saline irrigation solution 2 * Your plan may include Tiers 1a/1b. Refer to your pharmacy benefit summary for more information. Effective 08012025 56
 Anthem PPO & HDHP Essential Drug List Page 55 Page 57